
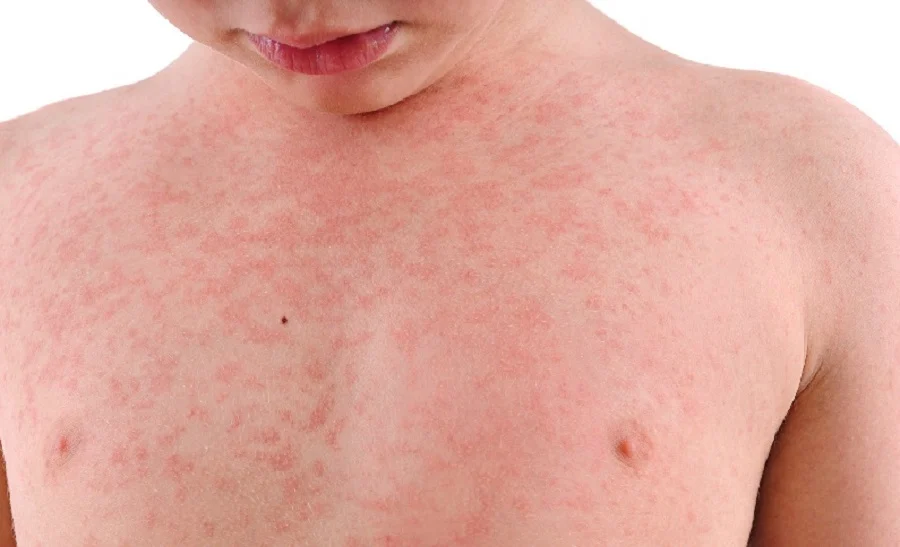
The humanitarian crisis in Bangladesh has reached a critical juncture as a relentless measles outbreak continues to claim the lives of the nation’s youngest and most vulnerable citizens. Official reports confirmed this week that the death toll has surpassed 1,000 children, a grim milestone that underscores the severe failure of public health infrastructure in the face of a highly contagious viral threat. Despite an aggressive, large-scale emergency vaccination campaign that has successfully reached over 19.8 million children, the epidemiological situation remains dire, with health authorities still logging approximately 1,000 suspected new cases every single day.
The escalation of the crisis, which gained significant momentum in March 2026, has overwhelmed local clinics and hospitals across the densely populated South Asian nation. With a population of 178 million, the structural limitations of the healthcare system have been laid bare, exposing deep-seated vulnerabilities that have been exacerbated by years of political instability, economic volatility, and the lingering shadow of the COVID-19 pandemic.
The Anatomy of the Outbreak
Measles is an acute viral respiratory illness characterized by high fever, cough, runny nose, and a distinct maculopapular rash. It is one of the most infectious diseases known to medical science, capable of spreading through the air via respiratory droplets long after an infected person has left a room. In Bangladesh, the transmission rate has been amplified by the country’s high population density, particularly in urban centers and impoverished rural districts where basic hygiene and sanitation resources are often limited.
Since March 2026, government health data indicates that over 194,000 cases of measles have been recorded. The virus, which can lead to severe complications such as pneumonia, encephalitis, and permanent blindness, has proven particularly lethal among children who missed their routine immunization schedules during the COVID-19 lockdowns. This "immunity gap" left millions of children without the necessary protection, creating a fertile ground for the current outbreak to flourish.
A Chronology of a Public Health Failure
The current crisis did not emerge in a vacuum. The roots of the epidemic can be traced back to the broader socio-political upheaval that has characterized Bangladesh over the last two years.
- 2024: Massive student-led protests erupt across the country, culminating in the ousting of long-term Prime Minister Sheikh Hasina. This period of civil unrest severely disrupted government operations, including the logistics of national health programs.
- Late 2024 – Early 2025: As the transitional administration under Muhammad Yunus took shape, bureaucratic shifts occurred within the Ministry of Health. UNICEF and other international observers noted that the procurement process for routine childhood vaccines faced significant delays during this transition.
- March 2026: The measles outbreak is officially declared, with cases surging across multiple districts. UNICEF labels the situation a "perfect storm," noting the convergence of low immunization coverage, political transition, and high population density.
- September 2026: The death toll crosses the 1,000 mark. Despite the implementation of emergency vaccination drives, the virus continues to circulate, with eight deaths reported on September 15 alone.
The Debate Over Vaccine Procurement
The controversy surrounding the availability of vaccines has become a focal point of the crisis. UNICEF, which acts as a primary supplier for many developing nations, has pointed toward the administrative delays during the change in government as a primary driver of the current supply shortage. According to reports from the UN agency, the transitional government opted to pause existing vaccine orders to review and potentially shift to new suppliers, a move that critics argue ignored urgent warnings from public health experts regarding the risks of an immunity gap.
Conversely, former officials within the Ministry of Health under the Yunus administration have consistently refuted claims of a systemic vaccine shortage. They argue that existing stockpiles were sufficient and that the distribution challenges were primarily logistical rather than a result of procurement policy. However, the sheer number of children continuing to contract the disease suggests a significant disconnect between central planning and on-the-ground immunization capacity.
Socio-Economic and Political Implications
The measles outbreak serves as a stark reminder of the fragile state of Bangladesh’s public health infrastructure. When a nation undergoes significant political transformation, essential services—most notably immunization programs—are often the first to suffer. The delay in procurement, whether due to a desire for administrative transparency or bureaucratic inertia, has had devastating, irreversible consequences for families across the country.
Furthermore, the outbreak highlights the persistent danger posed by the erosion of public trust in health institutions. In the wake of the 2024 protests, the public’s confidence in government initiatives has been tested. Combatting a viral outbreak of this magnitude requires not only the physical delivery of vaccines but also a robust public awareness campaign to counter vaccine hesitancy, which has seen a slight uptick in some regions due to misinformation spreading on social media platforms.
International Response and Future Outlook
The international community, led by the World Health Organization (WHO) and UNICEF, is currently providing technical and logistical support to the Bangladeshi health authorities. International aid has been focused on replenishing cold-chain storage facilities, training community health workers, and launching mobile vaccination clinics designed to reach the most remote, underserved communities.
However, health experts warn that the emergency response is only a temporary fix. To prevent future outbreaks, Bangladesh must revitalize its routine immunization program, which had been considered a global model of success prior to the 2024 political crisis. This includes investing in the digital tracking of immunization records, strengthening the supply chain for vaccine storage, and insulating public health initiatives from the whims of political instability.
The implications of this outbreak extend far beyond the immediate health crisis. It has forced a national conversation regarding the government’s responsibility to provide basic healthcare even during times of political transition. As the death toll continues to rise, the pressure on the current administration to demonstrate a more effective, science-driven approach to the crisis is mounting.
For the families of the 1,000 children who have lost their lives, the statistics are not merely data points; they are the result of a tragic intersection of biological vulnerability and institutional failure. The challenge for Bangladesh in the coming months will be to contain the current surge, restore the integrity of its immunization programs, and rebuild the public’s confidence in the institutions designed to protect the next generation.
As the vaccination drive continues, the government faces the daunting task of vaccinating the remaining millions of children who have yet to receive their dose. The success of this effort will depend on the stability of the supply chain, the dedication of the frontline healthcare workforce, and the willingness of the public to participate in the mass inoculation campaign. Until then, the nation remains on high alert, waiting to see if the measures taken will finally break the chain of transmission and bring an end to this devastating chapter in its recent history.
